A fistula is usually a persistent tunnel between the anal canal and nearby skin, left behind after an infected gland forms and drains an abscess. The operation you need depends on where that tunnel runs in relation to the anal sphincter, so you should expect diagnosis, mapping, treatment selection and recovery planning rather than a one-size-fits-all procedure.
Key takeaways
- MRI or examination maps the tract before choosing surgery.
- The operation must treat the fistula while protecting anal continence.
- Keep the wound clean and follow drainage instructions during recovery.
- Compare surgeon experience, procedure details and every item in the estimate.
How the surgeon confirms and maps an anal fistula
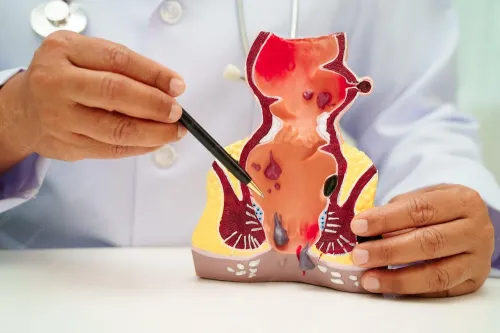
An anal fistula is an established tunnel from an internal opening in the anal canal to an external opening on the skin. It often follows an infected anal gland and abscess. Recurrent swelling, pus, blood or intermittent drainage from the skin opening suggests that the connecting tract remains active.
Draining an abscess relieves pressure but usually does not remove the tunnel. Antibiotics control infection; they do not normally close an established tract. The surgeon reviews your symptoms, inspects the skin, performs a digital rectal examination and uses proctoscopy to look inside the anal canal.
If pain prevents reliable examination, an examination under anaesthesia allows safer probing and mapping.
The surgeon classifies the tract by its relationship to the sphincter muscles:
- Intersphincteric: between the internal and external sphincters.
- Transsphincteric: crosses the external sphincter.
- Suprasphincteric: rises above the sphincter complex before descending.
- Extrasphincteric: lies outside the sphincters and reaches the rectum.
The amount of internal and external sphincter crossed determines whether the tract can be laid open safely; dividing too much muscle can affect continence. MRI pelvis is especially useful for recurrent, branching, horseshoe, high or clinically occult fistulas. Endoanal ultrasound can assess the tract and sphincter in selected cases.
Multiple, recurrent or unusually complex fistulas, or fistulas with diarrhoea, abdominal symptoms or other perianal disease, require evaluation for Crohn’s disease before planning a fistula in ano operation.
Which operation fits the tract and protects continence
The decisive question is how much sphincter the tract crosses. A simple low tract can often be laid open with fistulotomy and heal from its base; dividing more sphincter can improve cure rates but may impair control of gas or stool. Fistulectomy removes the tract, creates a larger wound and is not automatically better.
| Option | What it does | Typical role and limitation |
|---|---|---|
| Fistulotomy | Lays the tract open | Suitable low fistulas; avoid significant sphincter division |
| Fistulectomy | Removes the tract | Larger wound; not automatically more effective |
| Loose seton | Maintains drainage | Ongoing drainage or staged treatment for higher tracts |
| LIFT | Closes the tract between sphincter layers | Selected transsphincteric fistulas |
| Advancement flap | Covers the internal opening | Higher or complex disease while preserving sphincter |
| FiLaC or DLPL | Ablates the tract from inside | Sphincter-sparing option; long-term evidence is less certain |
| Ksharsutra | Gradually cuts and drains through the tract | Seton-based treatment requiring planned reviews |
A laser tract ablation is not automatically appropriate for a high, recurrent or branching fistula. An abscess usually needs drainage before closure, because sealing an infected cavity can recreate the problem.
If Crohn’s disease is involved, inflammation control and drainage may come before definitive repair; standard fistulotomy is not suitable for every Crohn’s-related fistula. The real decision in a fistula in ano operation is recurrence risk versus continence protection, not laser versus conventional surgery.
What happens during the fistula surgery process in Mumbai
1. Consultation starts with examination and a review of medicines, diabetes, smoking, allergies and previous operations. MRI pelvis, endoanal ultrasound or other tests are arranged when the tract is complex, recurrent or unclear. Follow bowel-preparation instructions if your surgeon requires them.
2. You receive written consent for the fistula in ano operation, including recurrence, bleeding, infection, a change in continence, staged treatment and a possible seton. Anaesthesia is selected for the procedure and your health, such as local, regional or general anaesthesia. The surgeon may then perform an examination under anaesthesia to map the tract safely.
3. During the operation, the surgeon identifies the external and internal openings, traces the main tract and branches, and drains any abscess. Based on the anatomy, the tract may be laid open, removed, ligated, closed or ablated. A fistulotomy wound is commonly left open so it heals from the base outward.
4. A loose seton may remain through the tract to maintain drainage or provide the first stage of treatment. A thread at the anus does not mean the operation failed.
5. In the recovery room, staff observe your breathing, pain, bleeding and vital signs. They provide pain control and check that you can urinate before discharge, with instructions for wound cleaning, medicines, dressings and follow-up.
The fistula surgery process in Mumbai may involve day-care or an overnight stay; that choice depends on the operation, anaesthesia, medical conditions, pain control and facility—not laser use alone.
Fistula surgery recovery: wound care, timelines and warning signs
Fistula surgery recovery usually includes soreness, light bleeding and drainage. An open fistulotomy wound heals from its base outward, while a loose seton can leave a thread and ongoing discharge to keep the tract draining; neither finding automatically means the operation failed.
1. Clean the area gently with water after each bowel movement and pat it dry. Warm sitz baths can ease soreness. Take the prescribed analgesia, drink adequate fluids, eat fibre, and follow the recommended stool-softening plan. The first bowel movements can hurt.
2. Daily activity often improves before the wound has healed completely. Time away from work depends on the procedure and your job; desk work and physical work have different demands. Complete healing can take several weeks.
3. Attend every follow-up. The treating surgeon will inspect healing, adjust or remove a seton, check for a persistent internal opening and decide whether a second-stage procedure is needed.
4. Contact the treating team promptly, or seek emergency care, for increasing pain or swelling, fever, spreading redness, heavy bleeding, inability to pass urine, rapidly increasing pus, a new painful lump or persistent recurrent drainage. Small amounts of drainage during the planned healing period can be expected, but recurrence can occur.
Do not ignore ongoing discharge after that period has passed.
How to choose a Mumbai surgeon and understand the estimate
Compare a fistula surgeon near me by the anatomical plan, not by the word “laser”. Ask:
- What is the fistula classification, and how much internal or external sphincter does it cross?
- Do I need an MRI pelvis or examination under anaesthesia, and what will each clarify?
- Why does fistulotomy, fistulectomy, a seton, LIFT, an advancement flap, laser or Ksharsutra fit this tract?
- What are your healing and recurrence rates for your own proposed method?
- What happens if I need a longer-term seton, staged treatment or a second operation?
| Option | Why it may fit | Main trade-off |
|---|---|---|
| Fistulotomy or fistulectomy | Low, simple tract; fistulotomy lays it open, while fistulectomy removes it | More sphincter division can affect continence; fistulectomy creates a larger wound |
| Seton or Ksharsutra | Drainage or gradual treatment of a tract unsuitable for immediate laying open | Requires planned reviews and possible further treatment |
| LIFT or advancement flap | Selected high or complex tracts where sphincter preservation matters | Healing and recurrence depend on tract anatomy and technique |
| Laser ablation | Attempts closure while preserving sphincter tissue | Long-term effectiveness is less certain; laser is not automatically appropriate |
Check the surgeon’s registration and qualifications in India’s National Medical Commission register. A technology label does not prove colorectal expertise. During consultations at Dr Manish Dhuris Advanced Laser Surgery or other Mumbai providers, require a written estimate separating surgeon fees, anaesthesia, operating-room or hospital charges, imaging, medicines, pathology, seton or laser consumables and follow-up.
There is no medically standard fistula package, so compare what each estimate includes. This is the practical core of fistula in ano surgery what to expect in Mumbai.
Related service
Fistula in Ano Surgery ₹1200 Fistula can operated by 1. LASER DLPL 2. Fistulectomy with LASER Ablation 3. Ayurvedic Ksharsutra Therapy View service → |
Frequently asked questions
How does a surgeon confirm and map an anal fistula?
The surgeon examines the external opening and anal canal, then uses imaging such as MRI when the tract is complex, recurrent or unclear.
Which operation is used for fistula in ano?
The procedure depends on the tract’s position and how much sphincter muscle it crosses. Options include fistulotomy, seton placement, LIFT and advancement flap surgery.
What happens during fistula surgery in Mumbai?
The team confirms the tract, administers anaesthesia, treats the internal opening and performs the selected procedure. You receive discharge and wound-care instructions afterward.
How long does fistula surgery recovery take?
Recovery depends on the operation and wound size. Follow cleaning and dressing instructions, attend review appointments and ask when you can resume work, exercise and driving.
Which warning signs require medical attention after surgery?
Contact your surgeon for fever, increasing pain or swelling, heavy bleeding, foul-smelling discharge, difficulty passing urine or worsening redness.
Keywords