
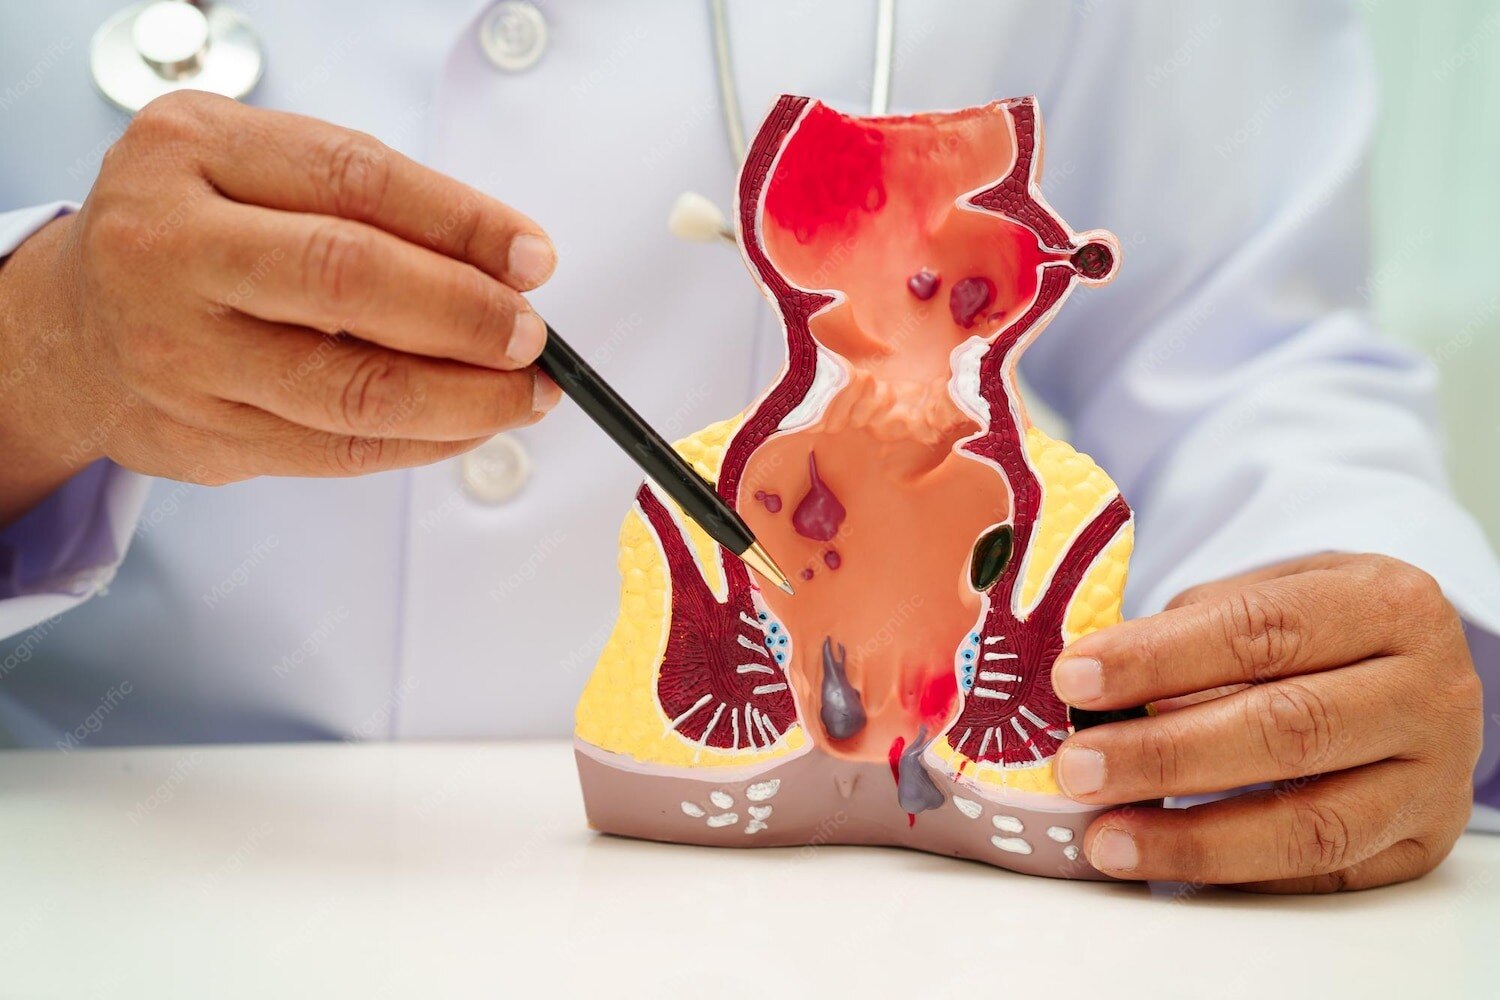
For a recent anal fissure, non-surgical care is usually the first step because many fissures heal when stools remain soft and sphincter spasm settles. Surgery becomes more reasonable when the fissure is chronic, keeps returning, or fails a properly followed medical plan. You will be able to compare the treatments, recognise warning signs and prepare useful questions for a Mumbai colorectal consultation.
Key takeaways
- Try fibre, fluids, stool-softening medicine and warm baths for a recent fissure.
- Arrange an examination if pain persists, bleeding recurs or healing does not begin.
- Surgery becomes more suitable for chronic fissures or failed medical treatment.
- Ask about anaesthesia, sphincter risks, wound care and your expected return-to-work date.
Which treatment should you try first: medical care or surgery?
Start with medical care for a first-time or short-duration fissure, not immediate surgery. An acute fissure is recent and often heals with fibre, fluids, stool-softening medicine when needed, and warm sitz baths.
A chronic fissure persists for roughly six weeks or more and may have a sentinel skin tag, hypertrophied anal papilla or visible internal sphincter fibres, which lowers the chance of healing through stool regulation alone.
| Option | Main advantage | Main limitation |
|---|---|---|
| Non-surgical care | Avoids an operation and continence risks | Requires consistent daily care and may fail |
| Lateral internal sphincterotomy | Most reliable healing for suitable chronic fissures | Dividing sphincter muscle carries flatus or stool-control risk |
Lateral internal sphincterotomy is not automatically the best first choice. The decision should reflect fissure duration, recurrence, bowel habits, response to a properly followed medical trial, continence history and previous anal surgery.
These factors matter when comparing anal fissure surgery or non surgical treatment in Mumbai, just as they do when reviewing anal fissure treatment options in Mumbai. A chronic fissure that repeatedly returns or fails medical care deserves specialist assessment; a recent fissure with improving pain usually deserves time and careful bowel regulation first.
How do you carry out non-surgical fissure treatment properly?
Non-surgical fissure treatment in Mumbai starts with making bowel movements soft and predictable, then maintaining that result every day. Anal fissure treatment options in Mumbai should be matched to your symptoms and examination, not stopped as soon as pain eases.
1. Increase fibre gradually to about 25 to 30 grams daily through vegetables, fruit, pulses and whole grains. Drink roughly 1.5 to 2 litres of fluid daily unless a clinician has restricted your fluids; adding fibre without enough water can worsen constipation.
2. If fibre and fluids do not produce soft, formed stools, ask a clinician about a prescribed stool-softening or osmotic laxative such as polyethylene glycol or lactulose. The target is easy passage, not diarrhoea.
3. Sit in warm water for 10 to 15 minutes after bowel movements or several times daily. A prescribed topical local anaesthetic can provide short-term pain relief, while glyceryl trinitrate, diltiazem or nifedipine relaxes the internal sphincter and supports healing. Glyceryl trinitrate can cause headaches; use only the prescribed formulation and directions.
4. Respond to the urge to open your bowels, avoid straining and keep toilet sitting brief. Continue the plan long enough to assess healing rather than stopping when pain improves. Pain relief alone does not prove that the fissure has closed, and hard stool can reopen it.
When should you stop self-treatment and seek an examination?
A clinician confirms a fissure through your symptom history and careful inspection. They ask about pain during or after bowel movements, bleeding, constipation, discharge and recurrence. If pain makes inspection intolerable, the examination may be limited; anoscopy or other tests are chosen only when they can be performed safely.
Seek prompt assessment if you have:
- Persistent bleeding, severe or worsening pain, fever, pus or swelling
- A recurrent fissure, even after a previous episode improved with home care
- Symptoms that do not improve with properly used treatment
- A fissure at the side rather than the usual front or back position
- Multiple, unusually large or painless lesions
- Diarrhoea, weight loss or another systemic symptom
The clinician distinguishes common alternatives by examining the lesion and surrounding skin. Haemorrhoids usually form swollen vascular cushions; a fistula leaves an opening or drainage track, while an abscess causes tender swelling, heat or fever. Diarrhoea and recurrent fissures raise concern for inflammatory bowel disease such as Crohn disease.
Ulcers or discharge can indicate a sexually transmitted infection, and a persistent painless ulcer or irregular mass requires assessment for anal cancer. Lateral, multiple, large or painless lesions can also reflect trauma, infection or malignancy, so do not select routine non surgical fissure treatment in Mumbai without investigation.
The right anal fissure treatment options in Mumbai depend on these findings, not symptom relief alone. Persistent or recurrent symptoms deserve review before you choose continued self-care or surgery.
When does anal fissure surgery become the better option?
Surgery becomes reasonable after an adequate, correctly used non-surgical trial fails, or when a chronic fissure persists, repeatedly returns, or causes pain that prevents normal bowel movements. For anal fissure surgery in Mumbai, the decision should follow an examination and continence-risk assessment, not pain severity alone.
| Option | What it does | Main trade-off |
|---|---|---|
| Lateral internal sphincterotomy | Divides a measured portion of the internal anal sphincter to lower resting pressure | Healing is commonly reported around 90–95%, but flatus leakage or stool-control problems remain possible |
| Botulinum-toxin injection | Temporarily relaxes the internal sphincter without cutting it | Lower healing and higher recurrence than sphincterotomy; repeat injection may be needed |
| Fissurectomy or advancement flap | Removes unhealthy fissure tissue, or covers the defect with healthy tissue | Useful when sphincter cutting is unsuitable, but healing and wound care require discussion |
Previous obstetric sphincter injury, baseline incontinence, inflammatory bowel disease and prior anal surgery require particular caution. A tailored or limited sphincterotomy, Botox, an advancement flap or continued medical care may be safer.
A “laser” label does not prove superiority. Ask what tissue is treated, whether the internal sphincter is cut, the expected recurrence rate and what evidence supports the method. Dr Manish Dhuris Advanced Laser Surgery can help match treatment to examination findings rather than the word laser alone.
For anyone comparing anal fissure surgery or non surgical treatment in Mumbai, the best option is the one that fits fissure duration, bowel function, sphincter status and previous operations.
Related service
Surgical Treatment ₹1200 *What is a Fissure-in-Ano?* A fissure-in-ano, also known as an anal fissure, is a small tear or cut in the lining of the anus. View service → |
What should you ask about anaesthesia, healing and returning to work?
The safer choice in anal fissure surgery in Mumbai starts with the recovery plan, not the word “laser.” Ask whether the procedure is day-care or requires admission, which anaesthesia is planned, and whether the surgeon proposes a standard or tailored sphincterotomy.
| Ask the clinic | What a clear answer includes | Why it matters |
|---|---|---|
| Procedure | A named operation, including whether the internal sphincter is cut | “Laser” alone does not explain the treatment |
| Continence | Assessment of baseline control, previous obstetric injury, prior anal surgery and sphincter risk | These factors can make standard sphincterotomy unsuitable |
| Recovery | Cleaning, bathing, dressings, pain relief, constipation prevention and follow-up instructions | Unclear wound care can delay healing |
| Discharge | A named contact for bleeding, fever, pus, urinary difficulty or worsening pain | You need help quickly if a complication develops |
Keep the area clean, follow bathing and dressing instructions, prevent hard stools, take prescribed pain relief and attend follow-up. Recovery varies by procedure and job: many patients resume light activity within days, while work should wait until the surgeon confirms that pain, bleeding and wound care are manageable.
Heavy lifting and strenuous exercise may need longer restriction.
Compare clinics on examination quality, the named procedure, complication discussion, follow-up access and willingness to offer non-surgical care—not “painless,” “laser” or “same-day” claims. The best anal fissure surgery or non-surgical treatment in Mumbai fits your fissure duration, diagnosis and continence risk, with a fallback plan if treatment fails.
Frequently asked questions
Which treatment should you try first for an anal fissure?
For a first-time or short-duration fissure, start with medical care: increase fibre and fluids, use stool-softening medicine when advised, and take warm sitz baths. Surgery is not usually the first step for an acute fissure.
How do you carry out non-surgical fissure treatment properly?
Keep stools soft with fibre-rich foods, adequate fluids and prescribed stool-softening medicine when needed. Avoid straining, do not delay bowel movements, and sit in warm water for about 10 to 15 minutes after bowel movements. Follow the treatment plan given by your doctor.
When should you stop self-treatment and seek an examination?
Seek an examination when severe pain, repeated bleeding, a lump, fever, pus, constipation or symptoms that persist despite treatment occur. A doctor should also assess recurrent fissures or bleeding because other conditions can cause similar symptoms.
When does anal fissure surgery become the better option?
Surgery becomes a stronger option when a fissure is chronic, keeps returning, or does not heal after properly supervised medical treatment. Your surgeon should confirm the diagnosis and discuss procedures such as lateral internal sphincterotomy, including continence risks.
What should you ask about anaesthesia, healing and returning to work?
Ask which procedure and anaesthesia you need, how pain will be controlled, how to keep the wound clean, when bowel movements are safe, which warning signs require help, and the expected date for returning to desk work or physical work.
Keywords




